


How to Shrink Acoustic Neuroma Naturally?
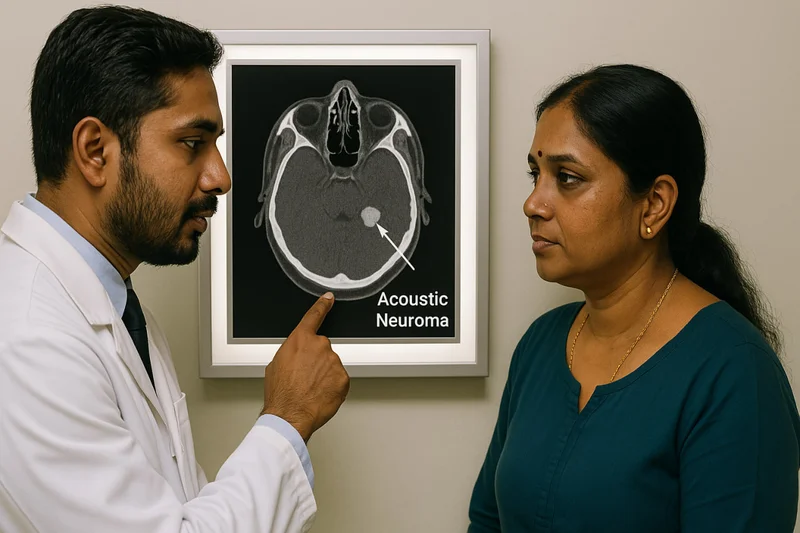
An acoustic neuroma — also known as a vestibular schwannoma — is a benign, slow-growing tumor that develops on the vestibulocochlear nerve (cranial nerve VIII) connecting the inner ear to the brain. Despite being non-cancerous, it can cause progressive hearing loss, tinnitus, balance problems, and in rare cases, life-threatening brainstem compression. About 2,000–3,000 new cases are diagnosed annually in the United States alone, with a global incidence of roughly 1–2 per 100,000 people per year. Treatment options range from careful observation ("watch and wait") to microsurgery and stereotactic radiosurgery — and the right choice depends on tumor size, symptom severity, patient age, and overall health.
This comprehensive guide covers everything you need to know: classification, symptoms, causes, diagnostic protocols, treatment comparisons, life after treatment, and questions most patients forget to ask. We've filled critical gaps that even top medical websites leave out — including the Koos grading system, tumor growth statistics, surgical approach comparisons, and quality-of-life data.
What Is an Acoustic Neuroma?
An acoustic neuroma is a tumor made up of Schwann cells — the cells that form the protective myelin sheath around peripheral nerves. It arises almost exclusively on the vestibular portion of the eighth cranial nerve, which is why the more accurate medical term is vestibular schwannoma. The tumor itself doesn't invade brain tissue; instead, it displaces and compresses surrounding structures as it grows.
Most acoustic neuromas grow at an average rate of 1–2 mm per year, though some remain stable for decades and a smaller percentage grow more aggressively (up to 10 mm/year in rare cases). A 2014 systematic review in Otology & Neurotology found that approximately 43–51% of observed tumors showed no measurable growth over a median follow-up of 3.2 years.
- Acoustic Neuroma vs Vestibular Schwannoma — What's the Difference?
Strictly speaking, there is no difference — they describe the same tumor. The term "acoustic neuroma" is a historical misnomer because the tumor doesn't arise from the acoustic (cochlear) portion of the nerve, and it's a schwannoma, not a neuroma. However, "acoustic neuroma" remains the more commonly searched and widely recognized term among patients, so most hospitals and patient-facing resources use both names interchangeably.
How Common Is Acoustic Neuroma? (Epidemiology)
- Incidence: Approximately 1–2 cases per 100,000 people per year worldwide.
- Age at diagnosis: Peak incidence is between ages 40 and 60, though younger patients are diagnosed more frequently now due to better MRI availability.
- Gender: Slightly more common in women than men (ratio approximately 3:2 in some studies).
- Bilateral tumors: Account for about 5% of all vestibular schwannomas, almost always associated with Neurofibromatosis Type 2 (NF2).
Acoustic neuromas represent roughly 6–8% of all intracranial tumors and about 80% of tumors in the cerebellopontine angle (CPA).
Tumor Grading and Classification (Koos Grades I–IV)
- No major competitor website presents the Koos classification in a patient-friendly format, yet it directly determines treatment strategy.
- Here it is:
| Koos Grade | Tumor Location & Size | Typical Management |
|---|---|---|
| Grade I | Small, confined to the internal auditory canal (IAC); usually <10 mm | Observation or radiosurgery |
| Grade II | Extends into the cerebellopontine angle (CPA) but doesn't touch the brainstem; ~10–20 mm | Observation, radiosurgery, or surgery |
| Grade III | Fills the CPA and contacts the brainstem without compressing it; ~20–30 mm | Surgery or radiosurgery (case-dependent) |
| Grade IV | Compresses the brainstem and/or causes hydrocephalus; usually >30 mm | Surgery strongly recommended |
The Koos system, introduced by neurosurgeon Prof. Wolfgang Koos in 1969 and subsequently refined, remains one of the most widely used classification frameworks in clinical practice.
Symptoms of Acoustic Neuroma
The symptoms of an acoustic neuroma typically develop gradually — sometimes over months or even years. Because the tumor grows slowly, many patients attribute early signs to aging or everyday stress, which can delay diagnosis.
Early Symptoms
- The most common initial symptom is unilateral sensorineural hearing loss (hearing loss in one ear). This is present in approximately 90% of patients at diagnosis.
- Other early signs include:
- Tinnitus (ringing, buzzing, or hissing in the affected ear) — reported in about 70% of cases
- Feeling of fullness or pressure in one ear
- Subtle balance difficulties, especially in low-light environments or on uneven surfaces
- Difficulty understanding speech on the phone when using the affected ear
A particularly telling sign is asymmetric hearing loss — when one ear hears noticeably worse than the other, especially for high-frequency sounds.
Symptoms as the Tumor Grows
As the tumor enlarges and presses on adjacent cranial nerves and the brainstem, symptoms become more pronounced:
- Facial numbness or tingling (trigeminal nerve, CN V compression)
- Facial weakness or paralysis on the tumor side (facial nerve, CN VII — though this is less common pre-operatively because the facial nerve adapts to slow compression)
- Persistent unsteadiness or vertigo
- Headaches — often occipital, sometimes with nausea
- Difficulty swallowing or hoarseness (lower cranial nerve involvement, seen with very large tumors)
- Hydrocephalus — blockage of cerebrospinal fluid flow, causing increased intracranial pressure. This is a medical emergency.
When to See a Doctor
You should seek medical evaluation if you notice:
- Sudden or progressive hearing loss in one ear
- Persistent tinnitus in one ear only
- Unexplained balance problems that are getting worse
- Facial numbness or weakness on one side
Don't wait. While acoustic neuromas are benign, delayed diagnosis of large tumors can lead to irreversible neurological damage.
What Causes Acoustic Neuroma?
- The exact cause of most sporadic (unilateral) acoustic neuromas remains unknown.
- However, the molecular mechanism is well understood: the tumor arises from a loss of function of the merlin protein (also called schwannomin), encoded by the NF2 gene on chromosome 22q12.
- Merlin acts as a tumor suppressor in Schwann cells.
- When both copies of the NF2 gene are inactivated — through somatic mutations — Schwann cells lose their growth regulation and proliferate, forming a tumor.
Neurofibromatosis Type 2 (NF2) and Schwannomatosis
NF2 is an autosomal dominant genetic disorder caused by an inherited (germline) mutation of the NF2 gene. It is the only well-established risk factor for acoustic neuroma.
- Patients with NF2 develop bilateral vestibular schwannomas — tumors on both sides — which is pathognomonic (definitively diagnostic) for the condition.
- NF2 affects approximately 1 in 25,000–33,000 live births.
- Symptoms typically manifest in the teens to early 20s, much earlier than sporadic cases.
- NF2 patients also develop other tumors: meningiomas, ependymomas, and schwannomas on other nerves.
A related condition, LZTR1-related schwannomatosis (formerly schwannomatosis), can also produce multiple schwannomas but characteristically spares the vestibular nerves.
Other Risk Factors
- High-dose cranial irradiation: A 2013 study published in the American Journal of Epidemiology found that prior radiation to the head and neck area — particularly in childhood — increases the risk of developing vestibular schwannomas later in life.
- Age: Risk increases with age, peaking in the 5th and 6th decades.
- Noise exposure and cell phone use: Despite widespread concern, large-scale studies — including the INTERPHONE study (2011) and a Danish cohort study of over 420,000 cell phone users — have not found a consistent, statistically significant link between cell phone use and acoustic neuroma risk. The evidence remains inconclusive but mostly reassuring.
Unilateral vs. Bilateral Acoustic Neuroma
| Feature | Unilateral (Sporadic) | Bilateral (NF2-Associated) |
|---|---|---|
| Frequency | ~95% of cases | ~5% of cases |
| Cause | Somatic NF2 gene mutations | Inherited germline NF2 mutation |
| Age at onset | 40–60 years | Teens to early 20s |
| Hearing preservation | Priority; multiple options | Extremely challenging; often leads to total deafness |
| Associated tumors | None | Meningiomas, ependymomas, other schwannomas |
| Genetic testing | Not typically needed | Recommended for patient and family members |
Bilateral vestibular schwannomas in a young person should immediately prompt genetic evaluation for NF2. Early identification allows proactive monitoring and potentially earlier intervention to preserve hearing.
How Is Acoustic Neuroma Diagnosed?
Diagnosis typically begins with a clinical suspicion based on unilateral hearing loss or tinnitus, followed by a combination of audiometric tests and imaging.
Audiometry and Hearing Tests
- Pure-tone audiometry: Measures hearing thresholds at different frequencies.
- Asymmetric sensorineural hearing loss — especially in the high frequencies — is a red flag.
- Speech discrimination testing: Many acoustic neuroma patients have disproportionately poor word recognition scores relative to their pure-tone thresholds. This is sometimes called a "retrocochlear pattern."
- Auditory brainstem response (ABR): Measures electrical activity in the hearing nerve and brainstem in response to sound. ABR can detect conduction delays caused by the tumor, though its sensitivity for small tumors is only about 70–90%.
MRI: The Gold Standard
- Gadolinium-enhanced MRI is the definitive diagnostic tool.
- The key sequences include:
- T1-weighted with gadolinium contrast: The tumor enhances brightly ("lights up"), making it easy to identify even at sizes as small as 2–3 mm.
- T2-weighted high-resolution sequences (CISS, FIESTA, or DRIVE): Provide excellent contrast between the tumor and surrounding cerebrospinal fluid in the IAC and CPA. These sequences can detect intracanalicular tumors without the need for contrast injection.
If MRI is contraindicated (e.g., certain pacemakers), a CT scan with contrast can be used, though it is less sensitive for small tumors.
Electronystagmography (ENG) and Videonystagmography (VNG)
These tests assess vestibular function by measuring involuntary eye movements (nystagmus). They are not diagnostic on their own but help evaluate the degree of vestibular impairment caused by the tumor.
Differential Diagnosis: What Else Could It Be?
Acoustic neuromas account for about 80% of CPA tumors, but other possibilities include:
- Meningioma (~10% of CPA tumors) — arises from the meninges, often has a "dural tail" on MRI
- Epidermoid cyst — appears differently on diffusion-weighted MRI
- Facial nerve schwannoma — rare, arises from CN VII instead of CN VIII
- Metastatic lesions — rare in the CPA but possible in patients with known systemic cancer
- Arachnoid cyst — CSF-filled cyst, easily distinguished on MRI
Getting the diagnosis right matters, because treatment approaches differ significantly between these entities.
Treatment Options for Acoustic Neuroma
- There is no single "best treatment" for all acoustic neuromas. The decision depends on tumor size, growth rate, the patient's hearing status, age, overall health, and personal preferences.
- A multidisciplinary team — including a neurotologist/otolaryngologist, neurosurgeon, and radiation oncologist — should ideally be involved.
Observation (Watch and Wait)
For small tumors (typically Koos Grade I–II) with minimal symptoms, active surveillance with serial MRI scans is a legitimate first-line approach.
- MRI is repeated at 6 months, then annually for several years, then every 2 years if stable.
- Suitable for elderly patients, patients with tumors in their only-hearing ear, or those with significant comorbidities.
- As mentioned, roughly 43–51% of tumors show no growth during observation periods of several years.
- If the tumor grows or symptoms worsen, treatment can be initiated.
This strategy avoids the risks of surgery or radiation entirely — but it comes with the psychological burden of "living with a tumor" and the small risk of delayed intervention reducing treatment outcomes.
Surgical Removal
- Surgery aims for complete (gross total) tumor removal while preserving facial nerve function and, when possible, hearing.
- Three surgical approaches are used:
Translabyrinthine Approach
- Access: Through the mastoid bone, directly through the inner ear structures.
- Hearing: Completely sacrificed — hearing in that ear is permanently lost.
- Best for: Any size tumor when hearing is already poor or non-functional.
- Advantage: Excellent facial nerve visualization; lower risk of facial nerve injury for large tumors.
Retrosigmoid (Suboccipital) Approach
- Access: Through a craniotomy behind the ear, accessing the CPA from behind.
- Hearing: Preservation is possible (roughly 30–50% success for smaller tumors with good preoperative hearing).
- Best for: Medium to large tumors; tumors with a significant CPA component.
- Disadvantage: Higher rate of postoperative headaches compared to other approaches.
Middle Cranial Fossa Approach
- Access: Through a craniotomy above the ear, lifting the temporal lobe to access the IAC from above.
- Hearing: Best chance of hearing preservation (50–70% in selected patients with small, laterally located tumors).
- Best for: Small intracanalicular tumors (Koos I) with serviceable hearing.
- Disadvantage: Limited exposure; not suitable for tumors larger than ~15–20 mm.
Comparative Table: Surgical Approaches
| Feature | Translabyrinthine | Retrosigmoid | Middle Fossa |
|---|---|---|---|
| Hearing preservation | No | Possible (30–50%) | Best chance (50–70%) |
| Tumor size suitability | Any | Medium–large | Small only (<15–20 mm) |
| Facial nerve outcome | Excellent for large tumors | Good | Good for small tumors |
| Post-op headache risk | Low | Higher | Moderate |
| Brain retraction | Minimal | Minimal to moderate | Required (temporal lobe) |
After surgery, complete tumor removal is achieved in approximately 95% of cases, with a recurrence rate of roughly 1–3% after gross total resection. The 5- and 10-year tumor control rates exceed 95%.
Stereotactic Radiosurgery (Gamma Knife / CyberKnife / LINAC)
Radiosurgery delivers a highly focused, single session of radiation to the tumor, aiming to stop growth rather than remove it.
- Best for: Small to medium tumors (generally <25–30 mm), patients who are poor surgical candidates, or patients who decline surgery.
- Tumor control rate: Approximately 92–98% at 10 years (tumor remains stable or shrinks).
- Hearing preservation: Around 50–75% at 5 years, declining to 30–45% at 10 years (varies by study and patient selection).
- Facial nerve preservation: >95% in most modern series.
- Side effects: Temporary swelling can cause transient symptom worsening. Rare risks include delayed hearing loss, facial numbness, hydrocephalus, and — very rarely — malignant transformation (estimated risk <1 in 1,000).
A 2019 meta-analysis in Journal of Neurosurgery confirmed that long-term tumor control rates with Gamma Knife radiosurgery are comparable to surgical resection for small-to-medium tumors, with lower procedural morbidity.
Medication: Bevacizumab (Avastin)
For NF2-associated vestibular schwannomas — particularly when surgery and radiosurgery carry unacceptable risks — bevacizumab, an anti-VEGF monoclonal antibody, has shown promising results.
- A landmark 2009 study in the New England Journal of Medicine reported tumor shrinkage in 55% of NF2 patients treated with bevacizumab, along with hearing improvement in some.
- It is not a cure; tumor regrowth can occur when the drug is discontinued.
- Side effects include hypertension, proteinuria, and impaired wound healing.
- Currently used off-label; not yet a standard first-line treatment for sporadic acoustic neuromas.
Prognosis and Life Expectancy
Acoustic neuromas are benign, and life expectancy is essentially normal for the vast majority of patients who receive appropriate management. Mortality is exceedingly rare with modern microsurgical techniques and radiosurgery.
Key prognostic data:
- Surgical mortality: <1% in experienced centers.
- 10-year tumor control after gross total resection: >95%.
- 10-year tumor control after radiosurgery: 92–98%.
- Recurrence after complete surgical removal: 1–3%.
- Recurrence after subtotal resection (intentional or unintentional): 18–30%, though many residual tumors remain stable for years.
The main long-term morbidity is not life-threatening but quality-of-life-threatening: hearing loss, chronic imbalance, facial nerve dysfunction, and fatigue.
Life After Treatment: Quality of Life and Rehabilitation
This is an area that deserves far more attention than it typically receives. Many patients expect to "return to normal" quickly after treatment, but recovery can be a longer journey than anticipated.
Adapting to Single-Sided Deafness (SSD)
- A significant number of patients lose hearing in the affected ear after surgery (or over time after radiosurgery).
- Coping with unilateral deafness involves:
- CROS hearing aids (Contralateral Routing of Signals): A microphone on the deaf side transmits sound to a hearing aid on the good ear.
- Bone-anchored hearing implants (BAHA/Ponto): Vibrate sound through the skull to the functioning cochlea.
- Cochlear implants: Increasingly explored for post-surgical cases if the cochlear nerve is intact, though outcomes vary.
Practically speaking, patients often struggle with locating the direction of sounds, hearing in noisy environments (restaurants, meetings), and feeling socially isolated. These challenges are real and should be discussed before treatment.
Vestibular Rehabilitation Therapy (VRT)
After tumor removal or radiation, many patients experience dizziness and balance difficulties because their vestibular system has been disrupted. VRT is a specialized physical therapy program that helps the brain compensate.
- Exercises include gaze stabilization, habituation exercises, and balance training.
- Most patients see significant improvement within 6–12 weeks of consistent VRT.
- A 2015 Cochrane review confirmed moderate-quality evidence supporting VRT for unilateral vestibular loss.
Chronic Fatigue and Cognitive Effects
An underreported consequence: many acoustic neuroma patients report persistent fatigue and difficulty concentrating — sometimes lasting months or years after treatment. A 2017 survey by the British Acoustic Neuroma Association found that over 60% of respondents identified fatigue as their most disabling long-term symptom.
The reasons are multifactorial — vestibular compensation demands cognitive resources, single-sided deafness increases listening effort, and the psychological toll of diagnosis and treatment is real.
Returning to Work and Driving
- Most patients return to desk-based work within 4–8 weeks after surgery; physically demanding jobs may require longer recovery.
- Driving can typically resume within 2–6 weeks, provided there are no significant balance or vision problems. Local regulations vary.
- Patients should be honest with themselves about their readiness — rushing back often leads to setbacks.
Pregnancy and Acoustic Neuroma
This is a question patients often raise but rarely find answered clearly.
Acoustic neuromas express progesterone receptors (and to a lesser extent, estrogen receptors). There have been case reports suggesting accelerated tumor growth during pregnancy, potentially related to hormonal changes and increased blood volume. However, large-scale evidence is limited.
Current clinical guidance:
- A known acoustic neuroma is not an absolute contraindication to pregnancy.
- Patients with a diagnosed tumor should undergo MRI before conception to establish a baseline, and monitoring should continue during or shortly after pregnancy.
- Delivery method (vaginal vs. cesarean) should be discussed with the neurosurgical team if the tumor is large or there are concerns about raised intracranial pressure during pushing.
- The decision is highly individualized. Getting a second opinion from a multidisciplinary skull base team is wise.
Second Opinions and the Multidisciplinary Approach
Acoustic neuroma treatment outcomes are heavily volume-dependent — meaning that centers and surgeons who treat many of these tumors per year consistently achieve better results.
A 2020 study in Otology & Neurotology found that hospitals performing ≥20 acoustic neuroma surgeries per year had significantly lower rates of facial nerve injury, CSF leak, and readmission compared to low-volume centers.
When to seek a second opinion:
- You've been told you need surgery but haven't been offered radiosurgery (or vice versa).
- Only one surgical approach has been discussed.
- You're unsure whether observation is safe for your specific tumor.
- Your surgeon performs fewer than 10–15 acoustic neuroma surgeries per year.
The ideal evaluation involves a neurotologist (otologist/neurosurgeon subspecialty), a skull base neurosurgeon, and a radiation oncologist — all reviewing your case together.
Current Research and Future Directions
- Science is not standing still on this front.
- Active areas of research include:
- Molecular-targeted therapies: Beyond bevacizumab, researchers are investigating MEK inhibitors, mTOR inhibitors, and other agents targeting the merlin/NF2 pathway (clinical trials ongoing as of 2024–2025).
- Gene therapy: Early-stage research into restoring NF2 gene function in Schwann cells.
- Robotic-assisted microsurgery: Emerging platforms aim to enhance surgical precision, particularly for facial nerve preservation during tumor removal.
- Improved hearing rehabilitation: Auditory brainstem implants (ABIs) are being refined for patients who lose the cochlear nerve, and outcomes are gradually improving.
- Liquid biopsy: Experimental work on detecting NF2 mutations in blood samples, which could eventually allow non-invasive monitoring.
The National Institute on Deafness and Other Communication Disorders (NIDCD) actively funds research in many of these areas.
Frequently Asked Questions (FAQ)
Is acoustic neuroma serious?
While acoustic neuromas are benign and not cancerous, they can become serious if left untreated and allowed to grow large enough to compress the brainstem. Very large tumors (Koos Grade IV) can cause hydrocephalus and become life-threatening. However, with timely diagnosis and appropriate management, the prognosis is excellent, and life expectancy is normal.
What is the best treatment for acoustic neuroma?
There is no single best treatment — it depends on tumor size, growth rate, hearing status, age, and patient preference. For small, non-growing tumors, observation may be all that's needed. For small-to-medium tumors, radiosurgery offers excellent tumor control with minimal invasiveness. For large tumors compressing the brainstem, surgery is usually necessary. The best treatment is the one recommended by an experienced multidisciplinary skull base team after evaluating your specific situation.
Can acoustic neuroma be cured without surgery?
Stereotactic radiosurgery (Gamma Knife, CyberKnife) can control tumor growth without surgery in approximately 92–98% of cases at 10 years. While it doesn't remove the tumor, it effectively stops it from growing. For NF2 patients, bevacizumab has shown the ability to shrink tumors in some cases. Observation alone is appropriate when the tumor is small and not growing. However, there is currently no medication that reliably cures or eliminates sporadic acoustic neuromas.
What is the life expectancy with acoustic neuroma?
- Life expectancy is essentially the same as the general population. Surgical mortality is below 1% at high-volume centers, and long-term tumor control rates (whether through surgery or radiosurgery) exceed 95%.
- The main concern is quality of life — specifically hearing, balance, and facial nerve function — rather than lifespan.
What is the difference between vestibular schwannoma and acoustic neuroma?
They are the same tumor. "Vestibular schwannoma" is the more anatomically and pathologically accurate term, while "acoustic neuroma" is the older, more widely recognized name among patients. Both are used interchangeably in clinical practice.
Do acoustic neuromas grow faster during pregnancy?
There is limited evidence suggesting that acoustic neuromas may grow faster during pregnancy, possibly due to hormonal influences and increased blood volume. However, this has not been conclusively proven in large studies. Patients with known tumors should discuss pregnancy planning with their treatment team and arrange baseline imaging beforehand.
Can alternative medicine treat acoustic neuroma?
- No alternative or complementary medicine has been scientifically proven to shrink or cure an acoustic neuroma.
- Some integrative approaches — such as acupuncture for tinnitus, yoga for balance, or mindfulness for anxiety — may help manage symptoms and improve quality of life, but they should never replace conventional medical evaluation and treatment. Be cautious of unsubstantiated claims.
Conclusion: Take the Next Step
An acoustic neuroma diagnosis can be overwhelming, but understanding your condition is the most empowering thing you can do. Most patients with acoustic neuromas lead full, normal lives after treatment — provided they receive care from experienced specialists and remain proactive about follow-up.
If you or someone you know is experiencing one-sided hearing loss, persistent tinnitus, or unexplained balance problems, don't delay seeking medical evaluation. An MRI with gadolinium can detect tumors as small as 2–3 mm and provide the clarity you need.
Ask your doctor about the Koos grade of your tumor, request a multidisciplinary evaluation, and don't hesitate to seek a second opinion. The right treatment decision — made with the right team — makes all the difference. This article is for informational purposes only and does not substitute for professional medical advice. Always consult a qualified healthcare provider for diagnosis and treatment decisions.
Scientific Sources
- Give me a kiss! An integrative rehabilitative training program with motor imagery and mirror therapy for recovery of facial palsy — Paolucci T et al., 2020, European journal of physical and rehabilitation medicine
- Risk Factors of Acoustic Neuroma: Systematic Review and Meta-Analysis — Chen M et al., 2016, Yonsei medical journal
- [[Application and development of super minimally invasive surgery concept in acoustic neuroma resection]](https://pubmed.ncbi.nlm.nih.gov/39266492/) — Zhang QJ et al., 2024, Zhonghua yi xue za zhi
- Diagnostics and therapy of vestibular schwannomas - an interdisciplinary challenge — Rosahl S et al., 2017, GMS current topics in otorhinolaryngology, head and neck surgery
- Ocular surface homeostasis instability in acoustic neuroma: corneal nerve density reduction and blink reflex abnormalities — Chen J et al., 2025, Graefe's archive for clinical and experimental ophthalmology = Albrecht von Graefes Archiv fur klinische und experimentelle Ophthalmologie
- Genetic variants of cancer‑associated genes analyzed using next‑generation sequencing in small sporadic vestibular schwannomas — Fujita T et al., 2023, Oncology letters
- Fully Endoscopic Resection of Cerebellopontine Angle Meningiomas — Setty P et al., 2016, Journal of neurological surgery. Part A, Central European neurosurgery
- RETRACTED: Brazilein induces apoptosis and G1/G0 phase cell cycle arrest by up-regulation of miR-133a in human vestibular schwannoma cells — Mou Z et al., 2019, Experimental and molecular pathology
- A novel method of translabyrinthine cranioplasty using hydroxyapatite cement and titanium mesh: a technical report — Bambakidis NC et al., 2010, Skull base : official journal of North American Skull Base Society ... [et al.]
- Electroacupuncture therapy for abducent palsy after acoustic neuroma surgery — Zhidan L et al., 2015, Acupuncture in medicine : journal of the British Medical Acupuncture Society
- Acupuncture for left lateral rectus muscle paralysis combined with facial nerve injury after acoustic neuroma surgery: a case report (https://pubmed.ncbi.nlm.nih.gov/41741991/) — Gu K et al., 2026, Zhongguo zhen jiu = Chinese acupuncture & moxibustion
- The aborted early history of the translabyrinthine approach: a victim of suppression or technical prematurity? — Nguyen-Huynh AT et al., 2007, Otology & neurotology : official publication of the American Otological Society, American Neurotology Society [and] European Academy of Otology and Neurotology
आयुर्वेदिक डॉक्टर से एक प्रश्न पूछें और मुफ़्त या सशुल्क मोड में अपनी चिंता की समस्या पर ऑनलाइन परामर्श प्राप्त करें।
2,000 से अधिक अनुभवी डॉक्टर हमारी साइट पर काम करते हैं और आपके प्रश्नों की प्रतीक्षा करते हैं और प्रतिदिन उपयोगकर्ताओं को उनकी स्वास्थ्य समस्याओं को हल करने में मदद करते हैं।
संबंधित आलेख








